Anion Gap Basics
The anion gap is a calculated value used to measure acid-base balance and detect hidden irregularities in serum electrolytes. It is derived from common blood chemistry values and helps clinicians spot an electrolyte imbalance that may not be obvious from a simple review of the electrolytes alone. In practice, the anion gap is often used as a diagnostic tool in the workup of metabolic acidosis and other metabolic disturbance patterns.
The calculation primarily uses serum sodium, serum chloride, and serum bicarbonate, with potassium sometimes included depending on the method or laboratory reference range used. Because the body contains charged particles, or ions, the difference between measured cations and measured anions can reveal an anion deficit or anion excess. That difference can reflect unmeasured acids, toxins, or protein changes such as albumin abnormalities.
Clinically, the anion gap is part of a broader clinical assessment and should be interpreted alongside symptoms, laboratory values, renal function, and the overall metabolic evaluation. The anion gap is not a diagnosis by itself, but it can direct attention to important causes of acid-base disturbance.
How the Anion Gap Calculator Works
An anion gap calculator simplifies the calculation https://anion-gap-estimator957.swiftnestly.com/posts/anion-gap-calculator-for-hospital-lab-interpretation by using the measured values from a serum chemistry panel or electrolyte panel. The standard formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Some versions also incorporate potassium, especially in older reference methods:
Anion gap = (serum sodium + potassium) - (serum chloride + serum bicarbonate)
The reason potassium is sometimes excluded is that it is relatively small compared with sodium, so including it usually modifies the result only modestly. Still, when you are using an anion gap calculator, it is important to know which formula is being applied so the result matches the expected reference interval.
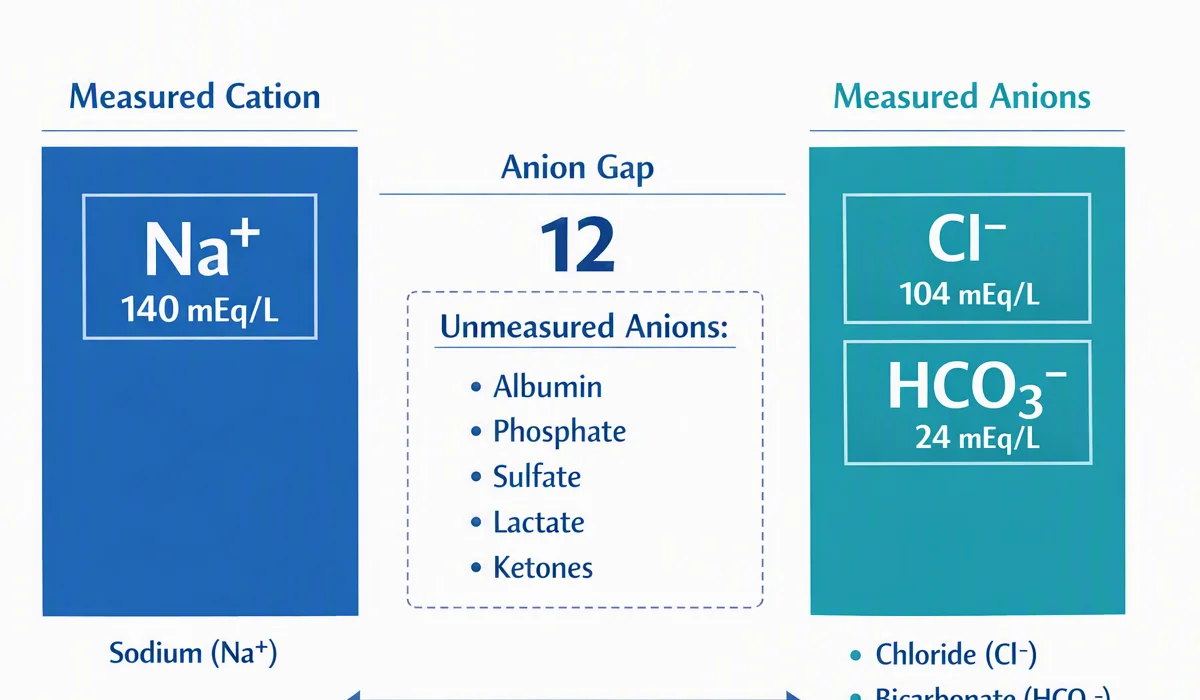
The calculator works best when the input values are accurate and come from the same blood draw. That matters because serum electrolytes can shift over time, especially during acute illness. The calculated result helps identify whether the patient has a normal or elevated gap and whether further workup is needed for an underlying metabolic disturbance.
Common inputs include:
- Serum sodium Serum chloride Serum bicarbonate Potassium, based on the method Albumin, if a corrected interpretation is needed
A quality calculator can also support interpretation by reminding the user that a change in albumin may alter the apparent anion gap, making albumin correction a key part of assessment in some cases.
Exploring Delta Anion Gap
The delta anion gap is a tool used to compare the degree of surplus unmeasured anions with the drop in bicarbonate. This may expose a mixed acid-base disorder that could be overlooked if you only review the standard anion gap. The related concepts of delta ratio and delta-delta are used to evaluate whether the change in gap is commensurate to the change in bicarbonate.
This approach is especially helpful in metabolic acidosis. If the gap rises because of additional acid load, bicarbonate should fall in a consistent way. If the relationship is not what you expect, it may point to another process is present as well, such as a concurrent normal anion gap metabolic acidosis or metabolic alkalosis.
The delta ratio is commonly determined as:

Delta ratio = (measured anion gap - normal anion gap) / (normal bicarbonate - measured bicarbonate)
The delta-delta concept is similar and often used interchangeably in clinical teaching. It compares the rise in anion gap to the fall in bicarbonate to evaluate whether the apparent acid-base change fits the expected pattern. This can be a useful way to identify a hidden second process affecting acid-base balance.
In simple terms, delta analysis asks: if there is an anion excess causing the gap to rise, did bicarbonate fall by the appropriate amount? If not, the patient may have a mixed disorder. That is important because a normal-looking pH or a partially corrected bicarbonate can mask a more serious problem.
Sequential Math Illustration
To understand how the anion gap calculator and delta analysis combine, it helps to review a simple example. Imagine the laboratory reference range for anion gap at a given institution is 8 to 12 mEq/L, and the standard formula uses sodium, chloride, and bicarbonate.
Sample laboratory values:
- Serum sodium: 140 mEq/L Serum chloride: 100 mEq/L Serum bicarbonate: 16 mEq/L Albumin: reduced
Applying the formula:
Anion gap = 140 - (100 + 16) = 24 mEq/L
This represents an elevated anion gap, since it is above the expected range. If the patient’s baseline or expected normal anion gap is 10 mEq/L, the delta calculation would be:
Delta AG = 24 - 10 = 14
Next, compare the fall in bicarbonate from a normal normal value of 24 mEq/L:
Delta bicarbonate = 24 - 16 = 8
Now calculate the delta ratio:
Delta ratio = 14 / 8 = 1.75
This value may suggest a predominantly elevated-gap process, though exact interpretation depends on the clinical context. If the ratio were much lower or much higher, that would point toward a mixed acid-base disorder.
It is also important to include albumin correction. Low albumin can lower the measured anion gap, making a true high anion gap metabolic acidosis look less obvious. Correcting for albumin can reveal a more accurate estimate of the patient’s acid-base state and help prevent missed diagnosis.
How to Interpret Delta Gap Results
Delta analysis is helpful because it links the anion gap with predicted bicarbonate changes. In a straightforward high anion gap metabolic acidosis, the elevation in anion gap should generally correspond to a matching decrease in bicarbonate. If that relationship is abnormal, the patient may have an underlying disorder.
Common assessment patterns include:
- Delta ratio roughly between 1 and 2: often consistent with a main high-gap acidosis Delta ratio less than 1: may indicate a concurrent normal anion gap metabolic acidosis Delta ratio greater than 2: may point to a concurrent metabolic alkalosis or chronic respiratory disorder with compensation
These patterns are not absolute diagnoses, but they are a practical framework for acid-base interpretation. The patient’s symptoms, vital signs, renal function, and other laboratory tests remain essential.
Respiratory compensation also matters. When metabolic acidosis develops, ventilation often increases to lower carbon dioxide. If the respiratory response is not suitable, a respiratory disorder may also be present. A careful interpretation should evaluate whether the patient’s breathing pattern fits the expected compensation for the degree of acidosis.
In clinical practice, delta gap results can show hidden complexity. For example, a patient may have lactic acidosis causing a high-gap acidosis and also diarrhea causing a normal-gap acidosis. Without delta analysis, the full picture of the acid-base problem may be missed.
Common Causes of Abnormal Anion Gap
Abnormal anion gap findings commonly suggest a harmful acid load or depletion of bicarbonate. The causes vary depending on whether the gap is elevated or normal.
Common causes of increased anion gap metabolic acidosis consist of:
- Lactic acidosis Ketoacidosis Renal failure Toxic alcohols
Lactic acidosis develops when lactate builds up due to hypoperfusion, sepsis, shock, seizures, or other causes of tissue oxygen imbalance. It is a leading cause of anion excess and can lead to pronounced metabolic derangement.

Ketoacidosis may be seen in diabetic ketoacidosis, alcoholic ketoacidosis, or starvation states. In these settings, ketone bodies elevate the anion gap while bicarbonate falls as buffering capacity is used up.
Renal failure can impair acid excretion and lead to retention of acids that expand the anion gap. In advanced kidney dysfunction, the ability to maintain normal acid-base balance is impaired, making serial monitoring important.
Toxic alcohols such as methanol, ethylene glycol, and related compounds can cause a dangerous acid load. These ingestions may appear with an elevated anion gap and require urgent recognition, especially when the clinical history is unclear.
On the other hand, normal anion gap metabolic acidosis often results from bicarbonate loss or impaired acid secretion. Causes include gastrointestinal bicarbonate loss, certain renal tubular disorders, or medication effects. Delta analysis helps reveal when both elevated-gap and normal-gap processes coexist.
Limitations and Medical Considerations
Although an anion gap calculator is a useful diagnostic tool, it has important limitations. The first is albumin correction. Because albumin is a key unmeasured anion, low albumin can lower the observed gap and conceal clinically important abnormalities. A corrected value may better reflect the true state of acid-base balance.
Laboratory error is an additional concern. Small measurement inaccuracies in sodium, chloride, or bicarbonate can affect the calculated result. For that reason, the anion gap should always be interpreted in light of the full clinical assessment and repeated if the result does not align with the clinical picture.
Different laboratories may use alternative methods, instruments, and laboratory reference range values. A normal result in one setting might be considered borderline in another. This is why the local reference interval matters when using the calculator for screening.
Further important considerations include:
- Changes in serum electrolytes over time can alter interpretation Chronic disease may dampen the expected response to an acid load Coexisting disorders can hide the primary process Clinical context should always direct the final interpretation
Ultimately, the anion gap and delta analysis should support, not replace, clinical judgment. They are especially useful when combined with history, exam findings, blood gas data, kidney function, and other laboratory results.
Common Questions
What is the anion gap formula?
The most frequently used anion gap formula is serum sodium subtracting the sum of serum chloride and serum bicarbonate. Potassium is included by some clinicians, depending on the method used by the laboratory. The calculation should follow the local blood chemistry reporting system so the result is interpreted correctly.
How is delta anion gap?
To work out delta anion gap, deduct the normal expected anion gap from the measured anion gap. Then compare that rise to the drop in bicarbonate from the normal expected value. This comparison is the basis of the delta gap formula and helps identify a mixed acid-base disorder.
What does an elevated delta ratio indicate?
A high delta ratio can suggest that the rise in anion gap is greater than the fall in bicarbonate would predict. That may indicate a concurrent metabolic alkalosis or chronic respiratory compensation pattern. The exact meaning depends on the full acid-base interpretation and the patient’s clinical status.
Why does albumin correction matter in anion gap interpretation?
Albumin correction is important because albumin is a major unmeasured anion. When albumin is low, the measured anion gap may appear falsely normal or only mildly elevated. Correcting for albumin improves the accuracy of anion gap analysis and can uncover a hidden high anion gap metabolic acidosis.
Is a mixed acid-base disorder still possible with a normal anion gap?
Yes. A normal anion gap does not rule out a mixed acid-base disorder. A patient can have a normal anion gap metabolic acidosis along with another process that offsets the gap, or a high-gap disorder that is partially masked by low albumin or another concurrent condition. That is why delta analysis, clinical context, and full blood chemistry review are so important.