How the Anion Gap Reflects in DKA
The anion gap is a laboratory-derived value that helps determine the cause of metabolic acidosis. In diabetic ketoacidosis, it is especially useful because it suggests the accumulation of acids that are not directly measured on a standard chemistry panel. This turns the anion gap a valuable diagnostic tool for recognizing high anion gap metabolic acidosis.
An anion gap calculator calculates the difference between the major measured cations and anions in the blood. The result helps clinicians assess serum chemistry data in the context of the patient’s acid-base balance. In DKA, the gap elevates as ketones accumulate and contribute unmeasured anions to the bloodstream.
Because DKA is an acidotic state, the body typically shows a low bicarbonate level along with an elevated anion gap. That pattern reflects ketone accumulation and a wider metabolic derangement. The anion gap does not diagnose DKA by itself, but it helps reinforce the diagnosis and tracks how the condition is shifting over time.
How to Work with an Anion Gap Calculator
An anion gap calculator uses a set of a few routine lab values from the electrolyte panel. You provide the serum sodium, serum chloride, and serum bicarbonate values, and the calculator uses the calculator formula to calculate the result.
The basic workflow is straightforward:
- Record the latest serum sodium value. Record the serum chloride value. Collect the serum bicarbonate value from the serum chemistry panel. Input the values into the calculator. Review the result alongside the rest of the laboratory results and clinical assessment.
This is important because DKA evaluation rarely depends on one number alone. The anion gap is part of a wider lab interpretation process that includes the patient’s symptoms, glucose level, ketone testing, pH, and treatment response. A calculator simplifies the math, but interpretation still requires clinical judgment.
Many clinicians rely on the result as a quick screen for metabolic acidosis and as a marker of resolution of acidosis during treatment monitoring. As the underlying ketoacidosis improves, the anion gap should trend toward normal and eventually show anion gap closure.
Anion Gap Formula and Normal Ranges
The classic anion gap formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
With this equation, the calculator determines the relationship between measured ions in the blood. Sodium is the primary measured cation, while chloride and bicarbonate are the principal measured anions included in the calculation. Any additional acids in the blood are often represented indirectly as unmeasured anions.
The normal anion gap range differs a bit depending on the laboratory method and the reference range used by that lab. That variation is why it is important to read the number in context rather than rely on a single universal cutoff. A mildly different result may still be normal if the lab’s reference interval differs.
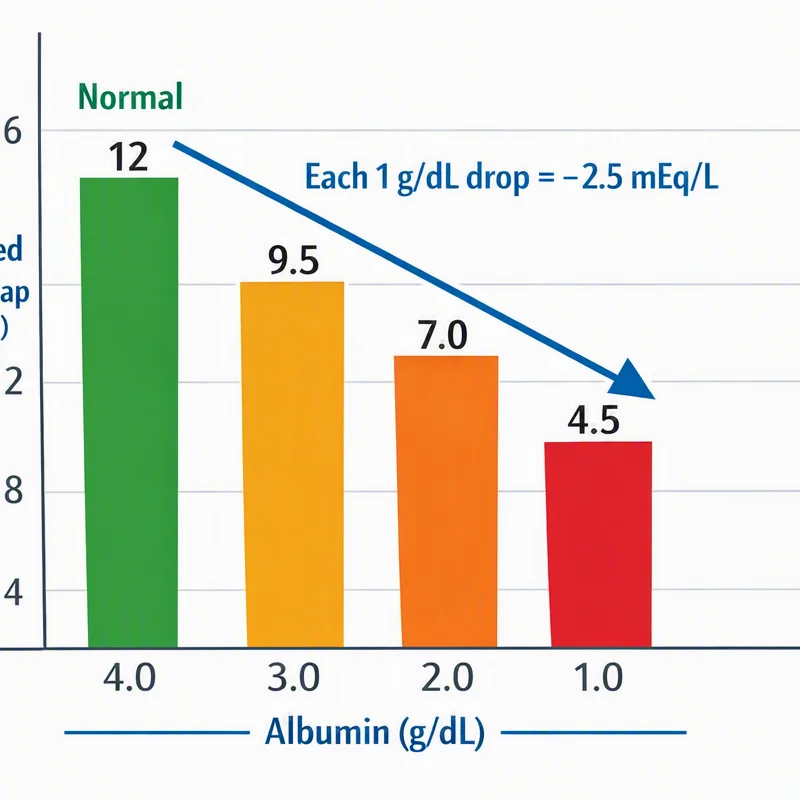
In practice, the anion gap should be interpreted with the rest of the electrolytes and with awareness of albumin correction. Albumin is a anion-like protein that affects the gap, so lower albumin can make the gap appear falsely low or normal. That is an important reason a raw value may not tell the full story.
Why the Anion Gap Is Raised in Diabetic Ketoacidosis
In DKA, reduced insulin leads to enhanced fat breakdown and formation of ketones, particularly acetoacetate and beta-hydroxybutyrate. These acids add to the blood as unmeasured anions, which increases the anion gap and contributes to ketoacidosis.
The process is a direct disturbance in acid-base balance. As ketones pile up, they consume bicarbonate, lowering the bicarbonate level and causing a metabolic acidosis with a high anion gap. This pattern is a recognizable hallmark of DKA and helps separate it from other forms of acidosis.
Beta-hydroxybutyrate is often the dominant ketone in severe DKA, so the degree of ketosis may be higher than a urine ketone test suggests. That is why the anion gap and direct ketone testing are complementary. Together, they show the patient’s acid burden more accurately than either test alone.
Adjusting the Anion Gap for low albumin
Albumin plays a major role in the measured anion gap because it is a important unmeasured anion in blood. When albumin is low, the anion gap may be too low. This is why albumin correction is often suggested, especially when the clinical picture suggests acidosis but the raw gap seems less concerning than expected.
Hypoalbuminemia can occur in many hospitalized patients and can mask a true high-gap process. In that setting, a corrected anion gap gives a better picture of the patient’s metabolic state. The corrected value helps avoid missing DKA or downplaying the degree of acid accumulation.
Although formulas for albumin correction can be slightly different, the goal is the same: modify the gap based on the measured serum albumin so the value better reflects the true acid burden. This matters because a normal-looking gap can be misleading if albumin is low. In DKA workups, the corrected value can improve lab interpretation and support better treatment monitoring.
Other Labs to Evaluate Together with the Anion Gap
The anion gap is only one part of the DKA workup. A meticulous evaluation also includes blood glucose, ketone body measurement, and acid-base testing. These studies aid in confirming the diagnosis and direct management.
An arterial blood gas or venous blood gas can reveal the pH and bicarbonate level, which reveal how severe the acidemia is. While venous testing is often adequate in many settings, the choice relies on the clinical context. Either way, the pH helps identify the acidotic state and contributes to the differential diagnosis.
Beta-hydroxybutyrate is especially valuable because it directly measures ketone burden. It can confirm ketone accumulation even when other markers are less clear. Blood glucose is also essential, but a normal or only mildly elevated glucose does not rule out DKA, especially in euglycemic presentations.
Reviewing these findings together builds a more complete picture of the metabolic derangement. The anion gap, blood https://anion-gap-analyzer011.yousher.com/how-to-interpret-an-anion-gap-calculator-when-albumin-is-low gas, glucose, and ketones should be interpreted as a group rather than as isolated laboratory results.
How the Anion Gap Changes During DKA Treatment
Care of DKA typically includes insulin treatment and IV fluids. As insulin suppresses ketone production and fluids support circulation and renal clearance, the anion gap should steadily fall. This trend is among the clearest signs that treatment is working.
During treatment monitoring, the clinician looks for anion gap closure, which suggests that the major ketoacid burden is resolving. The gap may normalize before the bicarbonate fully recovers, so it is important to consider the entire pattern rather than just one result.
Monitoring electrolytes is critical during this phase. Potassium, sodium, chloride, and bicarbonate can change rapidly as therapy progresses. IV fluids and insulin can also affect the apparent acid-base profile, so serial labs are needed to verify true improvement rather than a temporary lab shift.
As treatment continues, the goal is not only to lower glucose but also to correct the underlying acidosis. The anion gap helps show whether the ketoacid production has stopped and whether the body is returning to a stable acid-base balance.
Common Pitfalls & Interpretation Errors
One common pitfall is not recognizing a combined acid-base disorder. A patient with DKA may also have nausea and vomiting, impaired respiratory compensation, or another metabolic process that modifies the expected pattern. In those cases, the anion gap may not tell the whole story by itself.
Laboratory error is another concern. A single incorrect sodium, chloride, or bicarbonate result can alter the calculated gap and lead to misleading conclusions. If the number does not match the clinical picture, it is reasonable to run the test again and review the full electrolyte panel.
Hyperchloremic acidosis can occur during or after DKA treatment, especially after large volumes of chloride-containing fluids. This can lower the bicarbonate while the anion gap normalizes, making the metabolic picture look confusing. In that setting, the persistent acidosis may be due to chloride rather than ongoing ketone production.
Serum albumin also matters here. If albumin is low and not accounted for, the gap may appear falsely reassuring. Careful lab interpretation requires awareness of the corrected value, the clinical assessment, and the treatment timeline.
When a Normal Anion Gap Is Not Enough to Exclude DKA
A normal anion gap does not completely exclude DKA. One important example is euglycaemic DKA, where the blood glucose may be normal or only mildly elevated despite active ketoacidosis. This can happen in certain medication contexts or with reduced carbohydrate intake, and it requires a high index of suspicion.
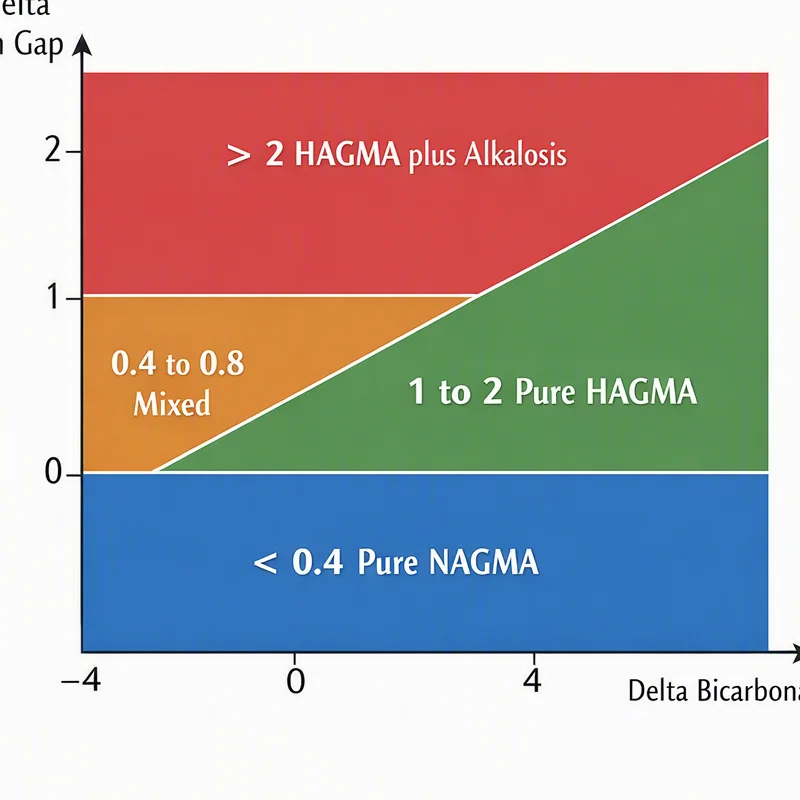
Another reason the gap may seem normal is that beta-hydroxybutyrate can remain elevated even when other markers are less dramatic. In early or partially treated disease, the anion gap may also begin to improve before the full metabolic picture resolves. That is why bedside assessment is so important.
If the patient still has symptoms and there is continued acidosis on blood gas testing, DKA can still be present even when the gap is not clearly elevated. In that setting, the differential diagnosis should include DKA, mixed disorders, and other causes of acidosis. The anion gap is valuable, but it is not a standalone rule-out test.
Frequently Asked Questions
What is the anion gap in diabetic ketoacidosis?
In diabetic ketoacidosis, the anion gap is a calculated laboratory value used to identify increased anion gap metabolic acidosis. It rises because ketones accumulate as unmeasured acidic anions, decreasing bicarbonate and enlarging the gap. It is used to aid diagnosis and monitor response to treatment.
What is the calculation for the anion gap from lab results?
Use the anion gap calculator or follow the anion gap formula: sodium minus the sum of chloride and bicarbonate. The needed values are blood sodium, serum chloride, and blood bicarbonate. The result should be interpreted with the rest of the serum chemistry and clinical findings.
What is the normal anion gap range for adults?
A expected anion gap range depends on the laboratory’s normal range and testing method. Because the ranges vary, the best approach is to compare the result with the lab’s stated normal limits instead of using one universal number. Albumin level may also influence what seems normal.
What is the reason for correcting the anion gap for albumin?
Correcting the anion gap for serum albumin because low albumin can make the gap appear falsely low or normal. With hypoalbuminemia, the measured value may underestimate the degree of acidosis. Correction for albumin helps produce a more accurate adjusted anion gap for lab interpretation.
Can diabetic ketoacidosis happen with a normal anion gap?
Yes, it can. DKA with normal glucose, early treatment, low albumin, or a combined acid-base disorder can make the gap appear normal even when DKA is still present. If symptoms, ketones, pH, and bicarbonate point to ongoing disease, the diagnosis should still be considered even with a normal gap.