What the anion gap calculates
The anion gap is a computed value that aids estimate the balance between measured electrolytes in the blood and the unmeasured ions that are not directly shown on a serum chemistry panel. It is often used as a diagnostic marker for acid-linked problems and other metabolic imbalance patterns. In simple terms, it helps clinicians look for clues about whether the body’s electroneutrality is being maintained as expected.
Blood contains positively charged particles, called cations, and negatively charged particles, called anions. The major measured cations and anions on routine serum electrolytes testing include sodium, chloride, and bicarbonate. Because the body must stay electrically balanced, any difference between the main measured ions can suggest the presence of unmeasured anions or other shifts in plasma chemistry. That difference is what the anion gap reflects.
The clinical significance of the anion gap is not that it diagnoses a single disease. Instead, it provides a framework for interpretation of lab results in the setting of illness, especially when evaluating acid-base disorder patterns. A high or low result may point to a broad range of causes, so the number must always be considered in diagnostic context with the patient’s symptoms and other blood chemistry findings.
Why sodium is a component of the formula
Sodium is included in the anion gap formula because it is the main measured cation in body fluid outside cells and a key contributor to plasma charge balance. In standard lab practice, the common formula is:
anion gap = sodium - (chloride + bicarbonate)Some versions of the formula may incorporate potassium, but sodium is the central analyte because it contributes most of the measured positive charge. The formula matches the main cation, sodium, against the main measured anions, chloride and bicarbonate. The difference offers an estimate of the amount of unmeasured negatively charged substances in the blood.
This is where the concept of electroneutrality becomes essential. The body’s fluids must remain electrically balanced, so the total positive and negative charges should roughly match. Since not all ions are directly measured, the anion gap uses sodium as the starting point for the calculation. Without sodium, there would be no easy way to estimate the gap between measured cations and measured anions.
The role of bicarbonate is also essential. When bicarbonate decreases, as it frequently does in metabolic acidosis, the calculated gap may rise if the lost bicarbonate is replaced by unmeasured acids. This makes the formula useful for identifying certain metabolic disturbance patterns that are not obvious from sodium alone.
How an Anion Gap Calculator uses sodium values
An Anion Gap Calculator is a useful tool that implements the formula automatically with your serum sodium, serum chloride, and serum bicarbonate values. The calculator carries out the calculation efficiently and reduces the chance of arithmetic mistakes during lab interpretation. It is especially useful when reviewing multiple lab values in a limited time or when comparing repeated results over time.
The calculator’s output represents a gap calculation based on common serum chemistry data. Because sodium is the main starting point, even slight changes in serum sodium can influence the final number. However, the effect is best interpreted in combination with chloride and bicarbonate rather than sodium by itself. A change in one analyte may shift the result while the underlying physiology remains steady or changes in the opposite direction.
For example, if sodium remains stable but bicarbonate falls, the calculated gap may rise. If sodium falls or rises significantly, the absolute gap may also shift, but interpretation depends on whether the change reflects an actual acid-base disturbance, dilution, water balance changes, or another clinical factor. That is why an Anion Gap Calculator is an estimate tool, not a standalone diagnosis.
In practice, the calculator helps organize lab results into a pattern that supports clinical reasoning. It can identify a possible abnormal result, but the next step is always to interpret the number in relation to the overall electrolyte panel, symptoms, and other findings.
How elevated sodium and reduced sodium can mean about the anion gap
Changes in sodium concentration may influence the anion gap in ways that are that are important in practice but not always easy to interpret. In hypernatremia, sodium is high, which can push the calculated value higher. In hyponatremia, sodium is low, which can decrease the result. However, the relationship is not purely numerical; it is also tied to hydration status, plasma concentration, and the broader state of acid-base balance.
Hypernatremia does not automatically mean a high anion gap disorder is present. A patient can have hypernatremia from dehydration or water loss without a main acid-base problem. Likewise, low sodium may reflect too much water relative to solute, endocrine issues, kidney-related problems, or other causes that do not directly produce a high anion gap or low anion gap. The key is to avoid treating the anion gap as a sodium-dependent metric.
Serum osmolality can assist put sodium changes into better perspective. Because sodium strongly influences osmolality, large shifts in sodium may indicate a broader disturbance in fluid distribution. That disturbance may coexist with an acid-base issue, but it does not prove one. The best interpretation combines sodium with chloride, bicarbonate, and the patient’s overall status.
When sodium is outside the normal range, it can also affect the perceived severity of an acid-base disorder. A calculated gap may appear elevated or smaller than expected because the baseline concentration of the dominant cation has changed. For that reason, a careful reviewer should ask whether the sodium abnormality is shaping the result, masking another issue, or simply occurring alongside it.
Main causes of a high anion gap
A increased anion gap usually suggests that unmeasured acids are present in excess. This finding is commonly seen in acid buildup, where bicarbonate is used up as it neutralizes acid. Because bicarbonate falls, the calculation leaves a larger gap between sodium and the measured anions.
One major cause is lactic acidosis, which occurs when lactate accumulates faster than the body can remove it. Lactate is an unmeasured anion in standard routine labs, so it can elevate the gap. This may happen in shock, poor tissue oxygen delivery, severe illness, or other conditions that alter metabolism and perfusion.
Another notable cause is ketone-related acidosis. In this condition, ketone bodies build up and contribute unmeasured anions. It is often associated with diabetes, prolonged fasting, or alcohol-related metabolic changes. The increase in unmeasured acids changes the blood chemistry pattern and can produce a distinctly elevated gap.
Kidney-related toxin accumulation from impaired kidney clearance is also a classic contributor. When renal function declines significantly, acids and other solutes that should be excreted can build up. This affects the blood’s balance of measured and unmeasured components, making the anion gap a helpful sign in the broader assessment of kidney-related metabolic disturbance.
Additional causes can include toxins, severe illness, and mixed disorders. Still, the core idea remains the same: a high gap usually means the body has retained acids or retained unmeasured anions that are not shown directly in the routine electrolyte values.
When a normal anion gap can still be deceptive
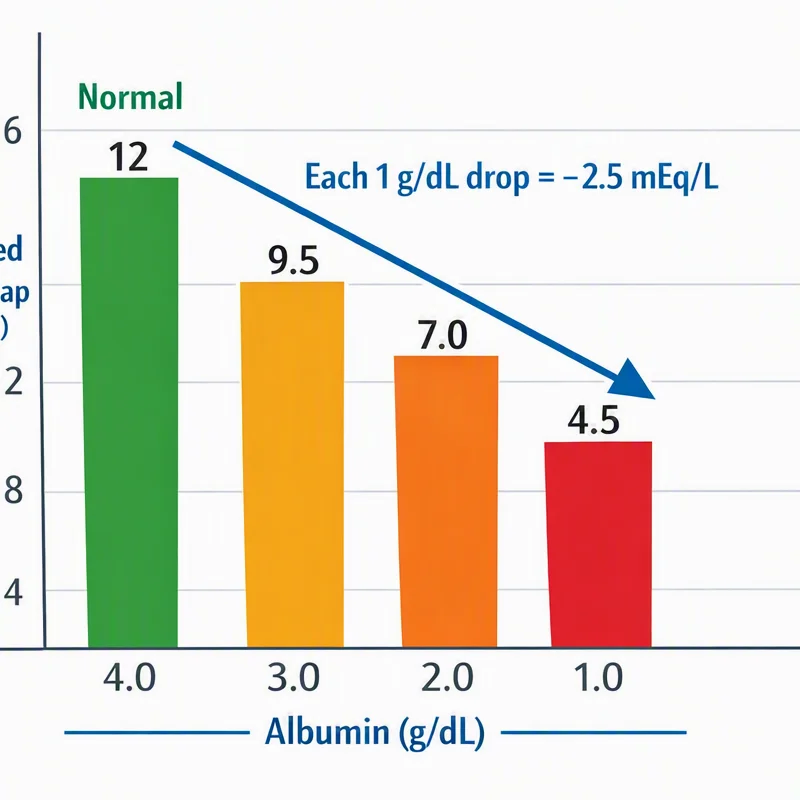
A routine https://anion-gap-calculation.com/calculators/delta-ratio.html result does not always mean the electrolyte picture is truly normal. A number of factors can make the anion gap look reassuring even when a serious problem is present. One major factor is albumin, the most abundant negatively charged protein in plasma. Because albumin contributes greatly to the usual gap, low albumin can obscure an elevated gap state.
This is why clinicians sometimes use a corrected anion gap. The correction compensates for hypoalbuminemia so the result better represents the real burden of unmeasured anions. Without this step, a patient with low albumin may appear have a normal gap even though a meaningful acid-base disorder is present underneath.
Lab error is another concern. Sample handling problems, measurement variability, or reporting mistakes can alter sodium, chloride, or bicarbonate values enough to affect the result. A suspicious number should always be rechecked against the full lab record and the clinical picture.
The chloride shift can also confuse interpretation. If chloride rises to offset another change, the calculated gap may stay within the expected reference range even when a significant process is occurring. In other words, the body may maintain apparent balance on paper while still undergoing a real metabolic change.

For these reasons, a normal gap should be viewed as one clue, not the final answer. It can be especially misleading in mixed disorders, low albumin states, or cases where fluid shifts alter measured electrolyte concentrations.
How to interpret results in the proper setting
The most accurate clinical interpretation of an anion gap result is based on combining it with the remainder of the patient’s data. Sodium, chloride, and bicarbonate reveal only some of the story. Additional information such as potassium, renal function, symptoms, medications, and the presence of illness all affect the meaning of the number.
An arterial blood gas is especially helpful when an acid-base problem is suspected. It gives information about pH, carbon dioxide, and compensatory changes that can clarify whether the patient has metabolic acidosis, respiratory issues, or a mixed disorder. In many cases, the anion gap is only one piece of the larger acid-base puzzle.
It is also important to check whether compensatory changes make physiologic sense. The body often responds to a metabolic disturbance with predictable respiratory or renal adjustments, but these responses may be incomplete or masked by another condition. That is why the calculated gap should be interpreted alongside symptoms, examination findings, and the overall serum electrolytes pattern.
In everyday practice, the best approach is to think in stages:
- Check whether sodium, chloride, and bicarbonate are abnormal. Establish whether the calculated gap is high, normal, or low. Examine albumin and consider a corrected anion gap when needed. Assess for renal impairment, lactic acidosis, ketoacidosis, or uremia. Confirm the result with broader clinical context and, when appropriate, arterial blood gas testing.
This stepwise approach strengthens lab interpretation and reduces the risk of overreading a single abnormal result. An abnormal result can be highly informative, but only when viewed as part of a complete diagnostic context.
Frequently asked questions about sodium and the anion gap
What is the role of sodium in the anion gap?
Sodium is the key checked cation used in the anion gap formula. It offers the foundation for the calculation, which compares sodium against chloride and bicarbonate to calculate the quantity of undetected anions in plasma. Without sodium, the calculation would not work as a reliable screening tool for electrolyte stability and acid-base disorders.
Why does the anion gap formula include sodium?
The equation features sodium because it is the dominant positively-charged analyte in routine serum electrolytes analysis. Since the body must maintain electroneutrality, sodium is used as the baseline for assessing measured cations with measured anions. This can help reveal hidden changes in blood chemistry that may point to metabolic disturbance.
Can low sodium affect the anion gap result?
Indeed. Hyponatremia can decrease the computed value because sodium is the primary input in the calculation. But the meaning of that change depends on the complete patient picture, including chloride, bicarbonate, serum osmolality, and whether there is a true acid-base disorder. Sodium by itself does not define the cause.
Can a normal anion gap exclude acid-base problems?
No. A regular result cannot eliminate all acid-base disturbances. Issues can be obscured by hypoalbuminemia, laboratory error, a chloride shift, or combined disorders. For this reason a normal value should be interpreted with the rest of the electrolyte panel, the patient’s symptoms, and any arterial blood gas results when available.
In what way does an Anion Gap Calculator assist in interpreting lab results?
An Anion Gap Calculator swiftly determines the anion gap calculation using serum sodium, chloride, and bicarbonate. It aids organize lab values, spot a possible elevated anion gap or decreased anion gap, and promote faster lab interpretation. Still, it does not replace clinical interpretation, since albumin, renal function, and the broader diagnostic context still matter.